
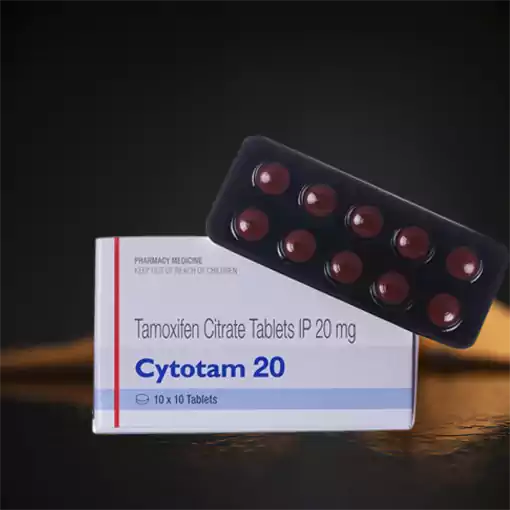
Tamoxifen was first made in 1962 by chemists at ICI Pharmaceuticals in the UK (now part of AstraZeneca). It was originally studied as a contraceptive, but researchers led by Dr. V. Craig Jordan showed it could block breast cancer growth. It was approved in the UK in 1973 and in the US in 1977, and remains one of the most prescribed cancer drugs in the world. It is now widely available as low-cost generics, as well as a liquid form (Soltamox).
Tamoxifen is a selective estrogen receptor modulator (SERM), the same family as raloxifene and clomiphene. It is a hormone therapy (endocrine therapy). It is not chemotherapy, not a steroid and not a hormone itself.
|
Property |
Detail |
|
Generic name |
Tamoxifen citrate |
|
Brand names |
Nolvadex, Soltamox (liquid), Genox, Tamofen, plus many generics |
|
Drug class |
Selective estrogen receptor modulator (SERM); anti-estrogen hormone therapy |
|
Chemical family |
Triphenylethylene (non-steroidal) |
|
Molecular formula |
C26H29NO (base); C32H37NO8 (citrate) |
|
Molecular weight |
about 371.5 g/mol (base); about 563.6 g/mol (citrate) |
|
Forms |
Tablets (10 mg and 20 mg); oral solution (10 mg/5 mL) |
|
Half-life |
About 5 to 7 days; its main active metabolite lasts about 2 weeks |
|
Prescription status |
Prescription only |
Tamoxifen itself is only a mild estrogen blocker. The liver converts it into much stronger active forms, mainly endoxifen and 4-hydroxytamoxifen, which are 30 to 100 times more potent. The key liver enzyme for this is CYP2D6. People whose CYP2D6 works less well, because of their genes or because of certain medicines, may make less endoxifen. This is why some drug interactions matter so much with tamoxifen (see the interactions section).
Because of its long half-life, it takes about 4 weeks of daily dosing for blood levels to become steady, and about 6 weeks after stopping for the drug to leave the body.
About 70 to 80% of breast cancers are estrogen receptor-positive (ER+). Their cells carry receptors that estrogen plugs into, sending a signal to grow and divide. Tamoxifen's active forms sit in those receptors and block estrogen from switching them on.
Unlike aromatase inhibitors such as Arimidex, which lower the amount of estrogen the body makes, tamoxifen blocks the receptor regardless of how much estrogen is around. So it works whether estrogen comes from the ovaries (before menopause) or from body fat (after menopause). This makes it the main hormone therapy for premenopausal women.
As a SERM, tamoxifen blocks estrogen in some tissues and mimics it in others.
|
Tissue |
Tamoxifen acts like |
Result |
|
Breast |
Anti-estrogen |
Treats and prevents ER+ breast cancer |
|
Uterus (womb lining) |
Estrogen (partial) |
Can thicken the lining; small rise in womb cancer risk after menopause |
|
Bone (after menopause) |
Estrogen |
Helps preserve bone density |
|
Bone (before menopause) |
Mild anti-estrogen |
May cause slight bone loss |
|
Liver |
Estrogen |
Lowers LDL cholesterol; raises clotting factors |
|
Brain (temperature control) |
Anti-estrogen |
Hot flashes |
Large combined analyses of clinical trials have shown that 5 years of tamoxifen in ER+ early breast cancer reduces the risk of recurrence by roughly half during treatment and lowers breast cancer deaths by about a third over 15 years. Taking it for 10 years instead of 5 lowers the risk further for many women.
|
Use |
Details |
|
Early breast cancer (adjuvant therapy) |
After surgery, to lower the risk of recurrence in ER+ cancer; used in pre- and postmenopausal women and in men |
|
Advanced or metastatic breast cancer |
To shrink or control ER+ cancer that has spread |
|
Ductal carcinoma in situ (DCIS) |
After surgery and radiotherapy, to lower the risk of invasive cancer |
|
Breast cancer risk reduction |
In women at high risk, such as those with a strong family history or certain biopsy findings |
|
Male breast cancer |
The standard hormone therapy for most men with ER+ breast cancer |
|
Off-label uses |
Painful or persistent breast enlargement in men (gynecomastia), some cases of male infertility, McCune-Albright syndrome in children, and ovulation induction in some countries |
Tamoxifen is taken by mouth once a day, with or without food. The doses below reflect standard prescribing information and are shown to explain how it is used. Your oncologist will confirm your dose and how long to take it.
|
Use |
Standard prescribing information |
|
Early breast cancer |
20 mg once daily for 5 years; often extended to 10 years |
|
Advanced (metastatic) breast cancer |
20–40 mg daily; doses above 20 mg split into morning and evening |
|
DCIS |
20 mg once daily for 5 years |
|
Breast cancer risk reduction |
20 mg once daily for 5 years |
|
Low-dose option (selected patients) |
5 mg daily for 3 years has been studied for some non-invasive breast conditions |
Some women switch from tamoxifen to an aromatase inhibitor after 2 to 5 years once they have gone through menopause. This is a common and effective approach your doctor may discuss.
Tamoxifen can make premenopausal women more fertile, even if periods become irregular. Use reliable non-hormonal contraception (such as condoms or a copper IUD) during treatment and for about 2 months after stopping, or longer if your doctor advises. Hormonal contraceptives are generally avoided in women with breast cancer.
The prescribing information carries a boxed warning for women using tamoxifen to treat DCIS or to lower breast cancer risk: it can cause cancer of the womb (uterine cancer), stroke and blood clots in the lungs, some of which have been fatal. For women with invasive breast cancer, the benefits of tamoxifen far outweigh these risks. For prevention, the balance depends on each woman's risk.
|
When |
What is checked |
|
Before starting |
Pregnancy test (if relevant), clot and stroke risk, gynecological history |
|
Yearly |
Gynecological review, breast imaging, eye checks if symptoms |
|
Any time |
Prompt assessment of abnormal bleeding, leg swelling, chest pain or vision changes |
|
Medicine |
Possible effect |
|
Strong CYP2D6 blockers: paroxetine, fluoxetine, bupropion, quinidine, cinacalcet |
Reduce conversion to endoxifen; may lower effectiveness. Usually avoided |
|
Safer antidepressant choices for hot flashes |
Venlafaxine, desvenlafaxine, citalopram or escitalopram are often preferred |
|
Warfarin and other coumarin blood thinners |
Strongly increased bleeding risk; close INR monitoring needed |
|
Aromatase inhibitors (anastrozole, letrozole) |
Not taken together; used in sequence instead |
|
Estrogen-containing products (HRT, birth control pills) |
Counteract tamoxifen |
|
Rifampin and other strong enzyme inducers |
Lower tamoxifen levels |
Tamoxifen is on the World Anti-Doping Agency (WADA) list of hormone and metabolic modulators, banned at all times. Athletes need a Therapeutic Use Exemption for medical use.
Many people take tamoxifen for years with manageable side effects. They are often worst in the first few months and may ease with time.
|
Problem |
What often helps |
|
Hot flashes |
Layered clothing, cool room, limiting alcohol and caffeine; some non-hormonal medicines that do not interfere with tamoxifen |
|
Vaginal dryness |
Non-hormonal moisturizers and lubricants; discuss other options with your oncologist |
|
Low mood |
Talk to your team early; choose antidepressants that do not block CYP2D6 |
|
Leg cramps |
Stretching, hydration, gentle activity |
|
Fatigue |
Regular light exercise, good sleep habits |
Get urgent medical help for:
The risk of womb cancer with tamoxifen is mainly in women after menopause and is about 2 to 3 times the normal risk, but the absolute risk remains low. Most cases are found early because of abnormal bleeding, so reporting bleeding quickly is the most important safety step.
Tamoxifen is a prescription-only medicine in the United States, United Kingdom, European Union, India, Australia, Canada and most other countries. It is not a controlled substance. Products sold online "for research" or for bodybuilding are unregulated, may be fake, and are used without the monitoring that keeps patients safe.
Nolvadex (tamoxifen) is a cornerstone of breast cancer care. Taken as a 20 mg tablet once a day, usually for 5 to 10 years, it blocks estrogen from fueling hormone receptor-positive cancer cells, cutting the chance of recurrence and death. It works before and after menopause and in men. Its common side effects, such as hot flashes and vaginal changes, are usually manageable, while rare risks such as blood clots, stroke and womb cancer can be caught early with good monitoring and prompt reporting of symptoms. Staying on treatment for the full course is one of the most powerful ways to protect your long-term health, so talk to your care team about any concerns rather than stopping on your own.
It treats hormone receptor-positive breast cancer in women and men, treats DCIS, and lowers the risk of breast cancer in people at high risk.
Yes. Nolvadex is the original brand name for tamoxifen citrate. Generic tamoxifen works the same way.
No. It is a hormone therapy that blocks estrogen's effect on cancer cells. It does not cause typical chemotherapy side effects like major hair loss or low blood counts.
Usually 5 years, and often up to 10 years for women at higher risk of recurrence. Some switch to an aromatase inhibitor after menopause.
Yes. It is the main hormone therapy for premenopausal women with ER+ breast cancer, sometimes combined with ovarian suppression.
Tamoxifen blocks the estrogen receptor and works before and after menopause. Arimidex lowers estrogen production and works only after menopause (or with ovarian suppression).
Some people notice weight gain, but large trials found little difference compared with placebo. Fluid retention, menopause changes and lower activity may contribute.
It can make periods irregular or stop them in some women, but it does not reliably prevent pregnancy. Non-hormonal contraception is needed.
Some, yes. Antidepressants that strongly block CYP2D6, such as paroxetine and fluoxetine, are usually avoided. Venlafaxine, citalopram or escitalopram are often preferred.
Yes. It is the standard hormone therapy for men with ER+ breast cancer and is used off-label for some men with breast enlargement.
Some use it to block breast tissue growth during steroid cycles or to restart natural testosterone afterward. This is unsupervised off-label use and carries risks such as blood clots, without medical safety checks.
There is no direct interaction, but alcohol can worsen hot flashes and slightly raise breast cancer risk. Keeping it low is wise.